
Gastrojejunostomy tube (GJ tube)
Feed past the stomach when it cannot keep food down.
A GJ tube enters the stomach through the belly wall, and a thin extension carries feeds past the stomach into the small intestine. We place it with X-ray guidance in about 30 minutes, and the feeding port can be used right away.
- Same day or overnight
- About 30 minutes
- Moderate sedation
- J port usable at once
 Fabio Komlos, MDInterventional radiologist
 Watch the video explanation21:46 video · Feeding Tube
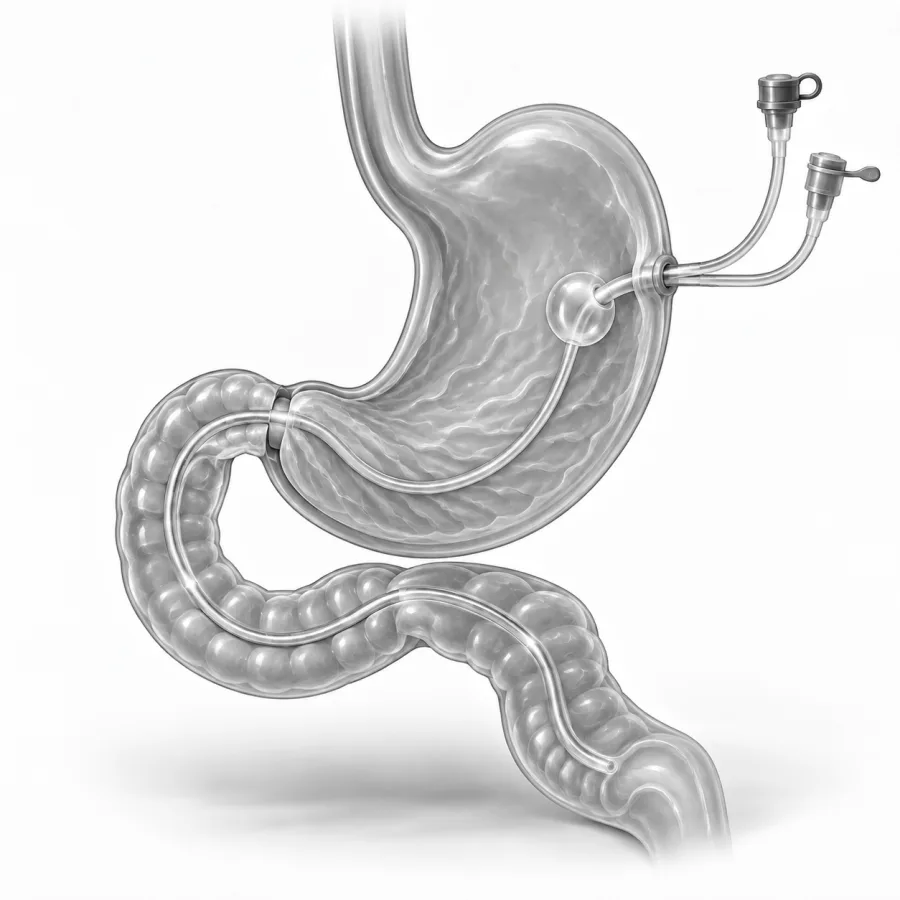
One port for the intestine, one for the stomach.
Feeding Tube
Dr. Fabio Komlos walks through gastrojejunostomy tube (gj tube) the way he explains it in clinic, using the same images he uses to plan treatment.
Fabio Komlos, MDInterventional radiologist · 21:46How do you take care of your feeding tube
8:06
Your First G-Tube: What Happens When You Don't Flush It Properly?
6:26
What is a GJ tube?
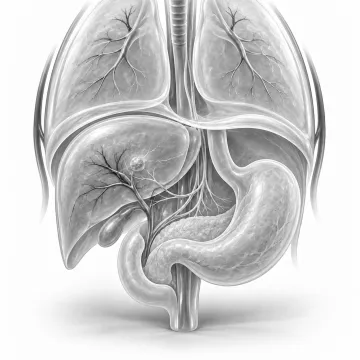
A gastrojejunostomy tube, or GJ tube, looks like a G tube from the outside. It passes through the belly wall into the stomach and is held by a water-filled balloon. The difference is a long, thin extension that continues out of the stomach, through the first part of the small intestine (the duodenum), and ends in the next part, called the jejunum.
The tube has separate ports. The J port delivers formula into the intestine. The G port opens into the stomach and is used to let out gas and fluid, called venting, and sometimes for medicines. A third small port fills the balloon. Each port is labeled.
On X-ray, the tube looks like a thin white line that loops through the stomach, curves around the C-shaped duodenum and ends past a landmark called the ligament of Treitz, in the upper small intestine.
Who needs one, and who may not
A GJ tube often helps if
- Your stomach empties very slowly, called gastroparesis
- You have bad reflux or vomit feeds given into the stomach
- You have a high risk of food going into your lungs (aspiration)
- There is a blockage at the outlet of the stomach, and the stomach needs venting while you are fed beyond it
- You need medicine absorbed steadily in the intestine, such as Duopa for Parkinson disease
Another option may be better if
How it compares with the alternatives
| G tube | GJ tube | Direct J tube | |
|---|---|---|---|
| Tip location | Stomach | Small intestine, through the stomach | Small intestine, directly |
| Feeding style | Syringe, gravity or pump | Pump, slowly | Pump, slowly |
| Stomach venting | Yes | Yes, through the G port | No |
| Upkeep | Least | Can clog or flip back into the stomach | Can clog; harder to replace |
| Placement | About 30 minutes | About 30 minutes | Longer and more complex |
GJ tubes can also be placed by a gastroenterologist with an endoscope, often called a PEG-J, or by a surgeon. If you already have a G tube with a healed tract, we can often convert it to a GJ tube in a short procedure through the same opening.
How to prepare
- Tell us about blood thinners. Some need to be paused. See blood thinners.
- Do not eat for 6 hours before. Clear liquids may be allowed until 2 hours before, unless we tell you otherwise.
- Bring a list of your medicines. Some pills cannot be crushed or given through a thin J tube, so your pharmacist may need to switch them to liquids.
- Plan for about 4 to 6 hours at the hospital, and for an adult to drive you home.
- Read before your procedure and sedation.
What happens, step by step
The procedure is done at El Camino Hospital with two nurses, a technologist and your interventional radiologist. Your heart rate, blood pressure and oxygen are watched throughout.
- 1Relaxing and preparing
Moderate sedation through your IV helps you relax. A thin tube is passed through your nose into your stomach, and the stomach is gently filled with air.
- 2Anchoring the stomach
After numbing the skin, we place 2 to 4 small anchors called T-fasteners to hold the stomach against the belly wall.
- 3Entering the stomach
A needle and guidewire enter the stomach between the anchors. The opening is gently widened.
- 4Guiding the tube into the intestine
Using X-ray, we steer a wire out of the stomach and around the duodenum into the jejunum. The GJ tube follows the wire, and the balloon is filled in the stomach.
- 5Checking and finishing
Contrast dye confirms the tip position. The outer disc is snugged to the skin and the nose tube is removed. The procedure itself takes about 30 minutes.
Recovery and care at home
- First hourYou recover while the nurses check your site and vital signs. Family can join you.
- Same dayThe J port can usually be used for feeding right away, starting slowly. No driving if you had sedation.
- Next dayYou may shower. Pat the site dry afterward.
- First weekSoreness fades over 2 to 3 days. Avoid heavy lifting and strenuous activity.
- 1 to 4 weeksThe T-fasteners fall off on their own. Throw them away.
Using the J port
- Feed through the J port with a pump, slowly. The intestine cannot hold a large amount at once the way the stomach can. Fast feeding can cause cramping, bloating and diarrhea.
- Flush the J port with water before and after every feeding and medicine, and every 4 hours during continuous feeds. Your team will tell you the exact amount, often 10 to 30 mL.
- Use liquid medicines when possible. The J tube is thin and clogs easily.
- Never force a flush. If it will not flush, try warm water with gentle pushes, then call us.
Using the G port
- Open the G port to a bag or syringe to let out gas and fluid if you feel bloated or sick, as your team instructs.
- Flush the G port with water daily, even if you do not use it.
Clean the skin daily with soap and water, and keep it dry. Check that the outer disc is snug. Do not rotate a GJ tube the way you might rotate a G tube, because twisting can move the J extension.
When someone keeps vomiting their tube feeds, I often recommend moving the feeding tip past the stomach. The GJ tube lets us feed the intestine and vent the stomach at the same time. I tell families that GJ tubes need a little more attention than a simple G tube, and that if feeds suddenly start coming back up, the J part may have slipped back into the stomach. That is a quick fix in the X-ray room.Fabio Komlos, MD, interventional radiologist · About Dr. Fabio Komlos
Risks and common problems
- Clogging is the most common problem, because the J extension is thin. A clogged GJ tube usually needs to be replaced in the X-ray room.
- The J extension can flip back into the stomach. Signs are vomiting formula or new bloating. We reposition or replace it under X-ray.
- Infection or irritation at the skin, usually treated with antibiotic pills.
- Leaking around the tube, often from a loose disc.
- Bleeding and peritonitis (infection inside the belly) are rare but serious.
- Dislodgement: the opening can start to close within hours if the tube comes out.
Common questions
Can I use the J port right after placement?
Why do I need a pump?
What if the tube clogs?
What if I start vomiting my feeds?
How often is the tube changed?
Will insurance cover it?
Feeding tubes
G, GJ and J tubes explained: why you might need one and how we place them.
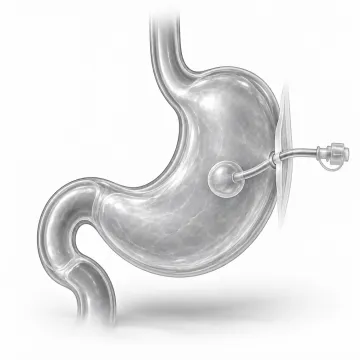
Gastrostomy tube (G tube)
A feeding tube into the stomach, placed with X-ray guidance through a small opening.
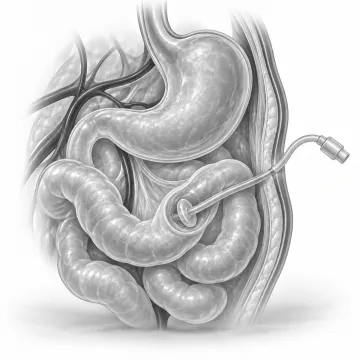
Jejunostomy tube (J tube)
A feeding tube placed directly into the small intestine, and tubes for Duopa therapy.
Palliative cancer care
Small procedures that ease fluid build-up, pain, blockages and eating problems caused by cancer.
Written for patients by the Palo Alto Interventional team. General information only; your own plan depends on your health and imaging.
Talk to us about your options
Request a consultation online, or call 650-404-8445, Monday to Friday, 8 am to 5 pm. You can also ask your doctor to send a referral. We will review your imaging and help you decide whether a procedure makes sense.